How to Build a Successful Spine Surgeon Collaboration?

How to Build a Successful Spine Surgeon Collaboration? begins with a practical truth: complex spinal care rarely succeeds through isolated expertise. It depends on coordinated decisions, shared responsibility, and patient-centered communication. Dr. Christopher I. Shaffrey, a leading spine surgeon and researcher, has described modern spine care as “a team sport.” That short phrase carries significant weight. A patient may meet a spine surgeon, neurologist, radiologist, physiotherapist, pain specialist, and operating-room team within one treatment pathway. Their decisions must connect.

Effective Spine surgeon collaboration is built in ordinary clinical moments. A radiologist flags subtle instability before the conference. A physiotherapist explains why a patient cannot climb stairs. A surgeon revisits the plan after hearing that concern. These details can prevent unnecessary procedures and improve surgical preparation. Clear referral criteria also matter. So do shared imaging protocols, documented consent discussions, and rapid communication after complications.

The process is not always smooth. Personal preferences can delay agreement. Hierarchies may discourage junior clinicians from speaking. Even experienced teams can overlook the patient’s daily reality. That weakness deserves attention, not concealment. A reliable collaboration model should welcome respectful disagreement, review outcomes, and examine near misses without blame. Short huddles help.

Trust grows through consistency. Teams should define who leads each decision, when opinions are requested, and how urgent changes are communicated. Patient goals must remain visible beside scans and operative plans. A successful collaboration is therefore more than cooperation between surgeons. It is a disciplined clinical system, measured by safer decisions, clearer explanations, and better recovery. Perfect teamwork is unrealistic. Deliberate improvement is not.

How to Build a Successful Spine Surgeon Collaboration?

Define the Goals and Scope of the Spine Surgeon Collaboration

A successful spine surgeon collaboration begins with a written purpose, not a vague promise to “work together.” Define the clinical problem, target patients, and expected benefit. Will the group reduce delays for complex referrals, improve surgical planning, or strengthen postoperative follow-up? Each goal needs a measurable signal, such as referral-to-consult time, complication review completion, or patient-reported recovery. Keep the list short. Too many goals weaken ownership.

The scope should describe where collaboration starts and stops. Set referral criteria, required imaging, urgent escalation rules, and responsibilities for surgeons, radiologists, therapists, nurses, and coordinators. Specify who leads case conferences and who records decisions. A shared timeline helps: referral within two business days, imaging review within five, and follow-up documentation after each visit. Protect patient confidentiality through approved systems and documented consent. Clinical judgment remains central. A checklist supports it; it cannot replace it.

Reliable partnerships also define evidence standards and review routines. Use current clinical guidance, local outcomes, and structured peer discussion when recommendations differ. Invite questions from every discipline. That matters. We once assumed a faster pathway meant a better pathway, but patients with unclear symptoms needed more assessment. The scope should allow exceptions, while requiring reasons to be recorded. Revisit the agreement quarterly, examine missed handoffs, and adjust roles when workload or patient needs change. Honest friction is useful.

Select Compatible Partners and Establish Shared Responsibilities

How to Build a Successful Spine Surgeon Collaboration?

Selecting compatible partners requires more than comparing surgical volume or credentials. A strong collaboration begins with shared clinical standards, communication habits, and patient priorities. Spine surgeons should examine how partners discuss uncertainty, manage complications, and respond to different opinions.

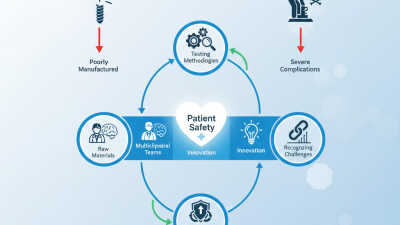
The World Health Organization’s Global Patient Safety Report 2024 states that about one in ten patients experiences harm in healthcare. More than half of this harm is considered preventable. That finding makes coordination a clinical responsibility, not an administrative preference.

Shared responsibilities should be written before the first complex case. One surgeon can lead imaging review, while another coordinates conservative treatment and rehabilitation. A designated surgeon should explain risks, alternatives, and expected recovery in plain language. The team must also define who answers urgent calls, reviews postoperative symptoms, and communicates with other specialists.

Brief case conferences can identify gaps before they reach the operating room. Short meetings work best.

The team should track complications, readmissions, reoperations, patient-reported outcomes, and delays in decision-making. The American College of Surgeons National Surgical Quality Improvement Program shows how structured outcome measurement can support surgical quality improvement. However, numbers alone cannot reveal every failure.

Our own weakness may be assuming that silence means agreement. A practical review should ask who missed information, where responsibility became unclear, and what will change next time. Honest reflection protects trust between surgeons and patients.

Create Standardized Clinical and Communication Workflows

How to Build a Successful Spine Surgeon Collaboration?

Create Standardized Clinical and Communication Workflows

A strong spine surgery collaboration begins with a shared clinical pathway. The pathway should define referral criteria, imaging requirements, neurological red flags, and review timelines. Each referral needs one clear owner. That person confirms missing information before the case reaches the surgeon. Small details matter. A dated symptom history, medication list, and focused neurological examination can prevent repeated appointments. Imaging should follow agreed protocols, with urgent findings flagged through a defined escalation route. Clinical judgment must remain central, because patients rarely fit perfectly into a checklist.

Communication needs the same structure. Teams can use a standard referral form, a concise case presentation, and a documented decision log. Every handoff should identify the next clinician, the required action, and the deadline. Read-back communication helps confirm high-risk information, especially after telephone discussions. Short weekly case reviews can expose delays, unclear roles, and inconsistent advice. Keep them focused. Patient-facing explanations should use plain language and match the documented treatment plan.

Our first workflow was too complicated. Staff skipped several fields, and surgeons received incomplete summaries. We revised the form after observing real consultations, not merely reviewing policy. That experience taught us to measure practical outcomes, including referral turnaround, cancelled visits, and patient-reported understanding. Monthly audits can reveal drift, while confidential feedback supports safer adjustments. A standardized process should guide decisions without replacing professional accountability.

Coordinate Patient Care, Data Sharing, and Quality Improvement

How to Build a Successful Spine Surgeon Collaboration?

Effective spine collaboration begins with a shared care plan. The plan should identify the lead surgeon, consulting specialists, and follow-up responsibilities. Before surgery, the team can review imaging, neurological findings, pain history, and patient goals together. Clear documentation reduces duplicated tests and conflicting advice. It also helps patients understand who will contact them after discharge.

Secure data sharing must support clinical decisions, not create more administrative work. Teams should use consistent terms for diagnosis, procedure, complications, and recovery measures. Access should follow professional roles and patient consent. Record key updates with dates, especially changes in weakness, bladder function, wound condition, or medication response. Small details matter.

Tips: Hold a short weekly case review. Use a standard referral template. Track readmissions, infection rates, unplanned returns, and patient-reported function. Compare results fairly across similar cases. Ask patients what felt confusing. Their feedback may reveal gaps that surgeons miss. Review the data every quarter, then test one practical improvement. No system is perfect. Even experienced teams may overlook delayed communication or assume that another clinician explained the risks. A brief audit can expose these weak points. The goal is not to blame individuals, but to make care safer, clearer, and more consistent.

How to Build a Successful Spine Surgeon Collaboration? - Coordinate Patient Care, Data Sharing, and Quality Improvement

A practical performance dashboard for coordinating multidisciplinary spine care, sharing actionable data, and driving measurable quality improvement.
Collaboration Dimension Performance Metric Operational Definition Reference Target or Benchmark Suggested Data Source Review Cadence Primary Improvement Action
Patient Care Coordination Referral-to-specialist appointment time Median number of calendar days from referral receipt to the first spine specialist consultation. ≤14 days for urgent referrals; ≤30 days for routine referrals Referral management system and appointment scheduling records Monthly Use standardized referral criteria, electronic triage, and reserved appointment capacity.
Patient Care Coordination Preoperative multidisciplinary case review rate Percentage of complex surgical cases reviewed by the agreed multidisciplinary team before surgery. ≥90% of eligible complex cases Case conference log and surgical scheduling system Monthly Define eligibility criteria and require documented consensus before scheduling high-complexity procedures.
Patient Care Coordination Complete clinical handoff rate Percentage of transfers containing diagnosis, imaging summary, neurological findings, medication list, and follow-up plan. ≥95% complete handoffs Electronic health record audit and standardized handoff checklist Monthly Adopt a structured handoff template with mandatory fields and closed-loop confirmation.
Patient Care Coordination Post-discharge follow-up completed within 14 days Percentage of surgical patients receiving a documented clinical or telephone follow-up within 14 days after discharge. ≥90% of eligible patients Discharge records, outpatient notes, and telephone encounter data Monthly Schedule follow-up before discharge and use nurse-led symptom screening for early escalation.
Data Sharing Imaging availability before consultation Percentage of referred patients whose relevant imaging and reports are available to the reviewing surgeon before the visit. ≥95% of consultations Picture archiving system, radiology reports, and referral records Monthly Use interoperable image exchange, a pre-visit checklist, and an escalation pathway for missing studies.
Data Sharing Structured clinical data completeness Percentage of records containing the agreed minimum dataset: pain score, neurological examination, functional status, imaging findings, and treatment history. ≥95% completeness Electronic health record audit and clinical registry Quarterly Embed structured fields in clinical documentation and provide feedback at surgeon and team level.
Data Sharing Patient-reported outcome measure completion Percentage of eligible patients completing a validated outcome questionnaire at baseline and at least one follow-up point. ≥70% at baseline and ≥60% at 12 months Patient portal, tablet-based questionnaires, or registry platform Quarterly Collect measures electronically, offer reminder messages, and provide language-access support.
Quality Improvement 30-day unplanned readmission rate Percentage of surgical admissions followed by an unplanned inpatient readmission within 30 days of discharge. Track risk-adjusted performance; investigate rates above the local baseline Administrative discharge data and electronic health record Monthly Perform structured reviews of readmissions and strengthen discharge education, medication reconciliation, and rapid-access follow-up.
Quality Improvement Surgical-site infection rate Percentage of eligible spine procedures complicated by a superficial or deep surgical-site infection within the defined surveillance period. Monitor against the institution’s risk-adjusted baseline and investigate any sustained increase Infection prevention surveillance and postoperative records Monthly Use standardized antimicrobial prophylaxis, skin preparation, temperature control, glucose management, and wound surveillance.
Quality Improvement Unplanned return to the operating room Percentage of index spine procedures requiring an unplanned reoperation during the defined postoperative period. Monitor by procedure type and risk-adjusted case mix Operating-room records and surgical registry Monthly Review every event using a multidisciplinary root-cause analysis and share learning without individual blame.
Quality Improvement Opioid prescribing at discharge Percentage of eligible patients whose discharge prescription follows the agreed procedure-specific dose and duration protocol. ≥90% protocol adherence Medication orders, pharmacy data, and discharge summaries Monthly Use procedure-specific defaults, multimodal pain management, patient education, and prescription review.
Quality Improvement Patient experience score Percentage of surveyed patients rating communication, care coordination, and discharge preparation as good or very good. ≥85% positive responses Standardized patient experience survey Quarterly Share results with the full care team and implement one documented patient-informed improvement per cycle.
Governance Action-item closure rate Percentage of quality-improvement actions completed by the agreed deadline and supported by documented evidence. ≥90% completed on time Quality-improvement project tracker and meeting minutes Monthly Assign one accountable owner, set measurable deadlines, and escalate overdue actions during the governance meeting.
Measurement note: Targets should be risk-adjusted and validated against local case mix, procedure type, patient population, and baseline performance. All patient-level data should be exchanged through authorized, secure systems in accordance with applicable privacy and data-protection requirements.

Measure Outcomes and Strengthen the Collaboration Over Time

How to Build a Successful Spine Surgeon Collaboration?

A strong collaboration grows when outcomes become shared evidence, not personal opinion. Teams should agree on a small measurement set before reviewing cases. Useful measures include pain scores, mobility, neurological function, complications, readmissions, and revision rates. Patient-reported outcomes add essential context. A technically successful procedure may still leave a patient unable to return to work.

Use consistent definitions and collection points. Record baseline status before surgery, then reassess at six weeks, three months, and one year. A simple dashboard can show trends without overwhelming the clinical team. Our first dashboard was too crowded. It delayed discussion instead of improving it. Fewer measures worked better.

Review the data during protected monthly meetings. Discuss unexpected results without assigning blame. A wound complication, delayed recovery, or missed follow-up can reveal a process problem. Compare results by procedure type and patient risk, while protecting privacy and obtaining appropriate consent. External benchmarks may help, but they should not replace clinical judgment. Each surgeon should explain variations, and colleagues should challenge assumptions respectfully. Document the agreed change, assign an owner, and check its effect at the next review. Small adjustments matter. A revised discharge checklist or earlier physiotherapy referral may improve recovery. Not every improvement will last, so teams should keep questioning their methods.